Translate this Page

Showing posts with label Virus. Show all posts

Monday, January 29, 2018

What is DRESS Syndrome?

DRESS (drug reaction with eosinophilia and systemic symptoms) is a poorly understood syndrome that has an unknown prevalence in the pediatric population because it is often missed by doctors. 
Symptoms include fever, an itchy rash covering over half the body, enlarged lymph nodes, and inflammation of the liver. A blood test reveals increased white blood cells, "atypical lymphocytes" (abnormally large and irregular lymphocytes because they are infected with the virus), and elevated eosinophils. 

What causes it? There have been links to both herpesvirus (including oral and genital herpes, epstein barr virus and roseola virus) and a couple months after starting certain anti-seizure medications. Bad cases will involve >90% of the skin and affect multiple organs such as the kidneys, and there may be involvement of the mucosal lining of the mouth and lips which can mimic life threatening drug and infectious reactions known as Stevens Johnson Syndrome and Toxic Epidermal Necrolysis.
It is very difficult to avoid getting this syndrome, as it is unknown why some patients get it and others do not. It can take months to fully recover from DRESS syndrome. The treatment, if caused by a medication, is to stop that medication. Most patients get IV or topical steroids to calm the immune system. 
Most often, pediatric rashes are harmless. In rare cases such as this, however, some detective work is required to make a swift and proper diagnosis.

Thursday, November 17, 2016

New Antibody Discovered Highly Effective Against HIV

A recent article in the Journal of Immunology highlighted a groundbreaking discovery in the fight against the human immunodeficiency virus (HIV). Funded by the National Institute of Health (NIH) and the National Institute of Allergy and Infectious Diseases (NIAID), Dr. Mark Connors and his team discovered an antibody named N6 that appeared to neutralize over 98 percent of the HIV isolates tested. What is particularly promising was the ability to eradicate even the known resistant strains.

To date, the discovery of a vaccine has been difficult due to the rapidly changing structure of the proteins on the surface of the virus. The N6 antibody, however, is particularly adept at binding a more consistent portion of the virus called the CD4 binding site, which allows it to attach to human cells.
The N6 antibody joins the ranks of the VRC01 antibody, which was discovered in 2010 and is in clinical trials, but it's effectiveness is far greater. This may translate to a vaccine that will finally prevent HIV from evading our immune system, saving countless lives and cutting healthcare costs. 


Tuesday, September 23, 2014

Ear Infection in Children

Ear infections are one of the most common disease processes seen by pediatricians. It is estimated that up to 85% of children suffer from at least one episode of ear infection before the age of 3.


The typical age range during which ear infections are seen is from 6 to 15 months old. Symptoms range from mild pain to hearing loss and brain abscess. There are three areas that become infected in the ear, and to understand this requires some knowledge of the anatomy:


The external or outer ear is where otitis externa (OE), also known as swimmer's ear, occurs. This is  is the only infection that causes pain with manipulation of the ear. The outer ear will usually be red and tender the the touch. The most common cause of this is a bacteria called pseudomonas, which thrives in wet conditions. The treatement for this, therefore, is over the counter ear drops that dry out the ear canal and make the area uninhabitable for the bacteria.

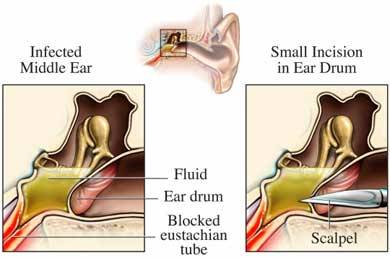
The middle ear is behind the eardrum or tympanic membrane. It is the space that houses the ear ossicles, the bones which transmit sound from the eardrum to the cochlea of the inner ear. This area is connected to the back of the nose (pharynx) via a hollow tube known as the eustachian tube.  An infection of this space is known as otitis media (OM). There are different types of OM, depending on the length of time it has persisted and whether or not fluid (effusion) is present.

Acute otitis media (AOM) typically occurs in <2 years old, usually caused by viruses such as RSV, cytomegalovirus (CMV) and Haemophilus influenzae (Hflu) but can also be due to bacteria. Mucosal congestion caused by the upper respiratory infection (URI) is aspirated up into the middle ear where inflammation occurs.
Treatment: If younger than 2 years old, an antibiotic such as amoxicillin will be prescribed. If older than 2 years old, doctors may choose to wait 48 hours to see if symptoms improve on their own before deciding to add an antibiotic. This is because studies have shown spontaneous resolution (without treatment) in up to 80% of this age group in 2-14 days.

Otitis media with effusion (OME) occurs when bacteria gets into the middle ear and fills it with pus. In growing children less than 7, the eustachian tube is often short and less vertical, so pus cannot drain properly and begins to back up. This growing pocket of fluid causes a large amount of pressure and pain to the child. The doctor will use a pneumatic otoscope to blow a burst of air at this ear drum. Normally the ear drum will move but in the case of OME, no movement occurs. Tympanometry may also be used to determine this. Long term OME (>3 episodes in 6 months or >4 episdoes in 12 months) may lead to hearing and language problems, so treatment is often indicated.
Treatment: myringotomy (hole is cut into the ear drum) with tympanostomy tube insertion is surgically performed. This allows fluid to freely drain out of the ear instead of backing up. It also alows antibiotic drops to be placed in the ear, which move through the tube and into the middle ear space to treat bacterial infections. Parents are instructed to apply the drops for 10 days whenever they see pus draining from the ears, which allows them to treat infections at home.


Reference
American Academy of Family Physicians, American Academy of Otolaryngology-Head and Neck Surgery, American Academy of Pediatrics Subcommittee on Otitis Media with Effusion. Otitis media with effusion. Pediatrics 2004; 113(5): 1412-29.

Friday, June 6, 2014

Protect Your Baby From Bronchiolitis

Bronchiolitis is a relatively common respiratory condition seen in children younger than 2 years old.  According to a recent study out of Finland published in the Scandanavian journal Acta Paediatrica, bronchiolitis is a major cause of lower respiratory tract illness and hospitalization in babies, especially those younger than 6 months old. The condition is mostly caused by the respiratory syncytial virus (RSV), which is the infectious agent in over 75% of cases.  Other viruses, including influenza (flu) and adenovirus represent the remaining 25% and in many cases exist as co-infections.


RSV season typically begins in October and ends in April.  The virus is spread via the hands of caregivers and other inanimate surfaces (fomites), and can stay alive on them for several hours. The virus enters the respiratory tract and infiltrates the top cell layer of the lungs, known as bronchiolar epithelium, causing inflammation and swelling and obstructing the small airways. Once this happens, air passing through these small spaces emits a whistle-like sound that can be heard as a wheeze outside of the body.

This wheeze, along with a runny nose (rhinitis), cough, and fever, is suggestive of  RSV bronchiolitis. It is important, however, for the pediatrician to rule out other disease processes, such as pneumonia or foreign body aspiration. Studies have shown that infants <12 weeks old, particularly those who were premature at birth, have an increased risk of requiring hospitalization and medical intervention. For many babies, though, this disease is self-limiting and no tests or treatments are necessary.

There are established risk factors for RSV that you can’t avoid; childcare attendance, school aged siblings, prematurity, congenital cardiopulmonary disease and immunodeficiency. But the steps listed below have been shown to reduce the risk of spreading RSV:
  • When in a group setting such as daycare or doctors offices, be sure that you and others caring for your children decontaminate their hands with alcohol-based sanitizer before and after direct contact with children or inanimate objects
  • Do not smoke tobacco or wear clothing that has been around cigarette smoke unless it has been thoroughly washed
  • Avoid exposing your infant to air pollutants
  • Always breastfeed your infant whenever possible to allow your infant's immune system to strengthen
  • Always follow current vaccination guidelines, including the flu vaccine


References
Bronchiolitis. Dynamed Database. Updated 2014 May 12 02:17:00 PM. Accessed June 6 2014. 


Pruikkonen H1, Uhari M, Dunder T, Pokka T, Renko M. Infants Under Six Months With Bronchiolitis Are Most Likely To Need Major Medical Interventions In The Five Days After Onset. Acta Paediatr. 2014 [Epub ahead of print]

Tuesday, June 3, 2014

How to Recognize Croup in Your Child

Pay close attention to your child’s next cough- it may suggest a common but serious childhood condition known as croup. Experienced pediatricians can recognize this particular cough in a crowded room; a sound often described as a “seals bark” that carries a potentially deadly omen. The medical term for this condition is laryngotracheobronchitis- a complicated word for inflammation of the upper respiratory tract, specifically the trachea and larynx.


Croup is most commonly caused by any one of several viral infections, including parainfluenza, influenza (flu), rhinovirus (common cold), adenovirus, respiratory syncitial virus (RSV), enterovirus and echovirus. In about 20% of cases, bacterial infections such as Mycoplasma pneumoniae, Corynebacterium diptheriae or staph or strep species are to blame.

The typical case of croup begins in a child under 6 years old between the fall and early winter months: The child has a history of an upper respiratory infection with fever and a cough that worsens at night.  The child's breathing becomes increasingly more labored, and a high pitched sound on inspiration known as stridor develops. This characteristic barking cough may follow:


How does this happen? When the upper airways become inflamed by an infection, swelling begins to narrow the passageway below the glottis through which air travels. As the airway narrows, our bodies attempt to compensate for poor airflow by increasing the respiratory rate (breaths per minute). The result is rapid air exchange through a narrowed airway (stridor), poor ventilation/oxygenation and respiratory distress.

It’s important that a pediatrician evaluates any child with stridor. Though many cases are self limiting and resolve in less than 48 hours, the doctor will rule out more serious conditions that present in a similar fashion, particularly epiglottitis, bacterial tracheitis and aspiration of a foreign budy. A simple oral dose of steroids (dexamethasone 0.15-0.60 mg/kg) will rectify the child’s breathing difficulties, though moderate to severe cases require inhaled (nebulized) racemic epinephrine.

  • A diagnosis of epiglottitis is more likely when the child is experiencing excessive drooling and leaning over in a “sniffing position”.
  • If the child is not treated, croup may lead to severe respiratory distress or become complicated with a pneumonia (known as laryngotracheobronciopneumonia)
  • There are reports of repeated cases of croup, known as  spasmodic croup, that may be caused by gastroesophageal reflux disease (GERD) or extreme sensitivity to the parainfluenza virus.
  • Any time your child is suffering from an upper respiratory infection, he or she is at an increased risk for developing croup


References
Croup. Dynamed Database. Updated December 27, 2013. Accessed June 2, 2014.

Petrocheilou A, Tanou K, Kalampouka E, Malakasioti G, Giannios C, Kaditis AG. Viral croup: diagnosis and treatment algorithm. Pediatr pulmonol. 2014; 49(5): 421-9.


Thursday, May 29, 2014

Pediatric autoimmune neuropsychiatric disorders associated with streptococcal infection (PANDAS)


Does a simple sore throat lead to psychological symptoms such as obsessive compulsive disorder (OCD) or Tourette syndrome?
In 1998, physicians began reporting odd encephalitis (brain inflammation)-like symptoms following an infection with Group A beta-hemolytic Streptococcus (GABHS), a bacterial infection.


Currently, PANDAS is not an ICD-9 recognized disease, and there is no recommended treatment. The suggested diagnostic criteria for PANDAS is abrupt onset (or dramatic exacerbations) of OCD or tic disorder, beginning between 3yo and the start of puberty, that occurs following an infection with GABHS. The neurologic examination would reveal hyperactivity, choreiform (snake-like) movements and/or tics.

Several studies have explored this phenomenon with conflicting results. Some authors found no correlation, while others found only elevated ASO (antibody) titers or the worsening of preexisting tic or OCD disorders. While some retrospective studies verified an association between infection and these neurological changes, a direct relationship has not been established.


Many clinicians think that PANDAS is simply a misdiagnosis of Sydenham’s chorea, a criteria for acute rheumatic fever (also caused by streptococcal infection) that is characterized by spastic and purposeless movements of the face or arms. Similarly to rheumatic fever, researchers believe that PANDAS may be due to the accidental production of antibodies that attack an area of the brain known as the basal ganglia.

  •  If your child develops a sudden tic or movement disorder, or begins to display uncharacteristic psychological behavior, it is important to contact your physician. While PANDAS may be only temporary, acute rheumatic fever can lead to serious heart problems.


Reference
Pediatric autoimmune neuropsychiatric disorders associated with streptococcal infection (PANDAS). Dynamed Database. Updated February 19, 2013, Accessed May 24, 2014.


Monday, May 19, 2014

MERS Virus Not Considered a Major Threat to the U.S.

Middle East Respiratory Syndrome (MERS) virus has made its way into the United States after killing hundreds in the Middle East. The MERS virus, first isolated in 2012, is a coronavirus that spreads through respiratory droplets and causes a severe acute respiratory illness. Symptoms of infection include fever, cough and shortness of breath.


MERS, similar to the flu, can be quite dangerous to the elderly and those with compromised immune systems. Since it’s transmitted following close human-to-human contact, family members caring for their sick relatives can easily contract the virus. This seems to be why so many have been infected in the Middle East: Owing to poor living conditions and the lack of proper medical care, an estimated 30% of those infected have died.

Two confirmed cases have been reported in patients traveling from the Arabian Peninsula to the United States.

On May 2, MERS was confirmed in an Indiana hospital. The patient, a healthcare worker, had recently arrived from Saudi Arabia following layovers in London and Chicago. He was isolated and successfully treated. Shortly after, an Illinois resident whom had close contact with the infected patient before his hospitalization began exhibiting symptoms of infection. He tested positive for antibodies to the virus, suggesting he suffered a very mild illness before fully recovering.

On May 11, MERS was reported in an Orlando hospital. The patient, a healthcare worker, was traveling from Saudi Arabia and reported layovers in London, Boston and Atlanta. He felt unwell during the flight, so visited the Emergency Room after landing. He was successfully treated and is currently in good health.


The current strain of MERS virus is not a major threat to the United States. Still, communities of immuno-compromised citizens in close quarters are at risk. It is for this reason that hospitals and nursing homes across states like Florida are warning residents to stay aware of the warning signs.

  • All viruses have the ability to mutate into a deadlier strain
  • There is no evidence of sustained spreading in community settings
  • If you’ve been in close contact with one of the individuals infected by MERS, call your healthcare professional and inform them promptly
  • Always wear a protective mask (such as N95) when caring for a patient or relative with a cough and a fever

Reference

Middle East Respiratory Syndrome (MERS). Centers for Disease Control and Prevention. Accessed May 19, 2014. http://www.cdc.gov/coronavirus/mers/index.html

Monday, May 12, 2014

The Importance of Identifying a Morbilliform Rash

The term "morbilliform" is used to describe any skin finding that resembles the measles rash. The macular lesions are typically diffuse, red and 2-10 mm in diameter. They may become confluent (come together to form clusters) in some areas. 


It is very important for doctors to know the differential diagnosis for a morbilliform rash, since some of the conditions are deadly. The process occurring within the body leading up to the rash, known as the prodrome, will help the physician narrow the diagnosis.This prodrome can be learned by ascertaining a good history. 

Some notable causes of morbilliform rash are:
  • Fifth Disease (erythema infectiosum/parvovirus B19/)
  • Sixth disease (roseola infantum/herpesvirus 6)
  • Streptococcal infection (Groups A, C)
  • Echovirus
  • Adenovirus
  • Kawasaki Disease
  • Rubella
  • Measles
  • Syphilis
  • Meningeal Petechiae (or Waterhouse Friedrichsen Syndorme)
  • Drug hypersensitivity Reaction (especially nevirapine, abacavir, phenytoin)


A study by Ramsay et al in 2002 evaluated the laboratory samples of 93 vaccinated children in England, and noted that the most common cause of the rash was a parvovirus B19 infection (17%). Group A strep was found in 15% of cases, and sixth disease (roseola infantum or herpesvirus 6) in 11%. None of the cases were caused by measles. The use of widespread vaccination has nearly eliminated the measles infection, making way for other viruses that cause similar rashes. It is paramount that physicians discern the cause of the findings.


Reference
Ramsay M, Reacher M, O'Flynn C, Buttery R, Hadden F, Cohen B, Knowles W, Wreghitt T, Brown D. Causes of morbilliform rash in a highly immunised English population. Arch Dis Child. 2002 Sep;87(3):202-6.

Monday, March 24, 2014

Is Ebola Coming To America?

The deadly Ebola virus has again struck the human race and attracted media attention in it's wake, particularly in the United States. For many, simply hearing or reading about Ebola evokes an uncomfortable and fearful feeling, partly due to media attention and movies like Outbreak but mostly because of the mystery that surrounds it. 

Is this virus as threatening to us as we make it out to be?


The Ebola virus likely begins it's life in African caves and mines within the bodies of fruit bats. Epidemics seem to begin when a single farmer or miner comes into contact with the infected animal. After seven days of incubation (virus making millions of copies of itself), the man develops sudden flu-like symptoms (headache, body ache, fever) and severe diarrhea that rapidly progress to cell death (necrosis), multi-organ failure, shock, widespread bleeding and, in many cases, death. Often, hospital staff or family members also become infected through contact with the patient's bodily fluids. 

Every couple of years, Ebola cuts through the middle of Africa like a knife, killing up to 88% of those it infects. It's monitored closely by the Center for Disease Control (CDC) for two important reasons: it easily spreads through the air (aerosol) and kills more than half of those it infects (high mortality rate). This is a harrowing combination for a virus but, despite it's label as a biosafety level 4 pathogen, it's currently not very threatening to the human race. Good sterilization and isolation processes help prevent rapid and deadly spread.

It's the fear of the unknown, though, that keeps scientists wary.

Ebola's lethal potential is recognizable in non-human primates: the virus has caused massive die-offs in gorilla and chimpanzee groups. It seems that the primates produce more infectious aerosol particles than do humans, attributing to the lethality. Luckily, these primate infections rarely spread to humans: only 25 human cases have been acquired from monkeys, with seven ending in death. The typical infection transmitted to humans from primates is more on par with a common cold. If this virus were to acquire the same virulence (or lethality) in humans as in monkeys, the results would be catastrophic. For now, however, it seems that Ebola is a manageable illness with little threat to the Americas.

  • There are five known species of Ebola, each named for the regions where they were originally identified.  The first reported cases in 1967 included 550 humans in Zaire and Sudan. The Zaire Ebola virus recurred in Gabon in 1994, causing 317 cases. The Sudan Ebola species returned in 2004, but this time in Uganda, killing 224 (53%) of 425 patients. 
  • The inflammatory response caused by the virus often leads to the body losing all it's platelets (used to plug holes), resulting in bleeding through multiple orifices.  It is for this reason it is known as a "hemorrhagic fever"
  • A new Ebola vaccine has been developed, but low funding has halted human trials. It may be as long as 20 years before the vaccine is commercially available. 


References

Peters CJ. Chapter 197. Ebola and Marburg Viruses. In: Longo DL, Fauci AS, Kasper DL, Hauser SL, Jameson J, Loscalzo J. eds. Harrison's Principles of Internal Medicine, 18e. New York: McGraw-Hill; 2012.http://accessmedicine.mhmedical.com.ezproxy.hsc.usf.edu/content.aspx?bookid=331&Sectionid=40726956. Accessed March 22, 2014.